This website is being reviewed and updated in line with the National Medical Commission (NMC) guidelines on ethical advertising and public communication by registered medical practitioners.
Banner for hernia surgery: blue left panel with text, orange curves, and a cross‑section of abdominal tissue with mesh on the right.

Colorectal Surgery in Ghaziabad: Conditions, Diagnosis and Treatment

Colorectal surgery is the surgical treatment of conditions of the colon, rectum and anus, including colon cancer, rectal cancer, anal fistula, piles and anal fissure. It can be done as open, laparoscopic or robotic surgery, depending on the condition and the patient. Surgery is advised only when medicines or other treatments are not enough, or when the condition, such as cancer, needs it.

Bowel and anal problems are easy to put off. People wait, hope the bleeding stops, try a cream, and carry on. Sometimes that’s fine. Sometimes it isn’t, and the only way to know is to get examined. This page explains how common colorectal conditions are assessed and treated, and what decides the choice of operation.

Banner advertising a colorectal surgeon in Ghaziabad with Dr. Shashank Agrawal on the right, arms crossed, maroon curved design, and headings: 'Expert Care for Your Digestive Health' and 'Colorectal Surgeon in Ghaziabad'; four icons below highlight Advanced Laparoscopic Surgery, Expertise in Colorectal Conditions, Personalised Treatment Approach, and Compassionate Care for Better Outcomes.

What Is Colorectal Surgery?

Colorectal surgery covers operations on the large intestine, rectum and anus. The range runs from common problems like piles and fissures to colon and rectal cancers. The treatment depends on the diagnosis, its severity, the symptoms and the patient’s general health. Where possible, the plan tries to protect normal bowel function and, in rectal and anal surgery, the sphincter muscles that control continence.

Not sure whether you need a gastroenterologist or a surgeon? Read gastroenterologist vs GI surgeon: who treats what.

Conditions covered on this page:

Colon cancer
Rectal cancer
Anal fistula
Piles (haemorrhoids)
Anal fissure

Colorectal Cancer: Colon and Rectum

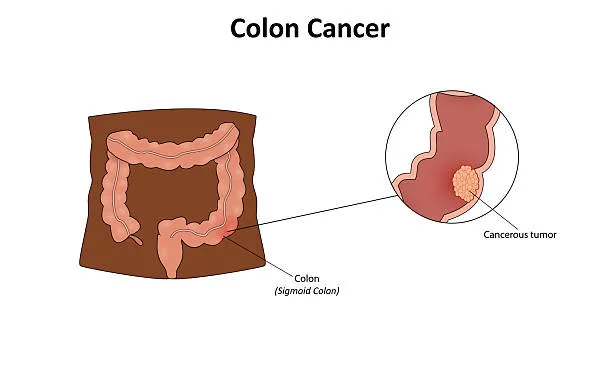
Diagram of the large intestine showing the sigmoid colon and a magnified view of a cancerous tumor in the colon wall, indicating colon cancer.

Colon Cancer

Colon cancer begins in the large intestine, often from a polyp that changes over time. Planning starts with a colonoscopy and biopsy to confirm the diagnosis. A CT scan of the chest, abdomen and pelvis shows whether the disease has spread, and a blood test for CEA is often done as a baseline. Together these give the stage (using the TNM system), which guides treatment.

Read More..

Surgery (colectomy) removes the section of colon carrying the tumour, with its blood supply and the lymph nodes that drain it. The surgeon then joins the two ends of bowel, which is called an anastomosis. A temporary stoma is sometimes needed, for example in an emergency with blockage. After surgery, the removed tissue is examined under the microscope. This report, including the lymph node findings, decides whether chemotherapy is advised.
Read more about colon cancer treatment.

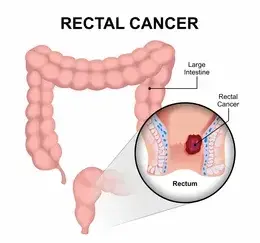
An anatomical diagram of the large intestine highlighting rectal cancer in the rectum with a magnified inset showing a tumor.

Rectal Cancer

The rectum sits in the narrow space of the pelvis, close to the sphincter muscles, bladder and nerves for urinary and sexual function. This is why rectal cancer is planned differently from colon cancer. An MRI of the pelvis shows how far the tumour is from the anal opening and whether it is close to the surrounding tissue layer, known as the mesorectal fascia. 

Read More..

Some patients are advised radiotherapy, with or without chemotherapy, before surgery. This is decided by a team that includes the surgeon, oncologist and radiologist.

The standard operation is total mesorectal excision (TME), which removes the rectum together with the fatty tissue around it. Depending on the tumour’s position, this may be a low anterior resection, where the bowel is rejoined, or an abdominoperineal resection, where a permanent stoma is needed. Tumours close to the sphincter are the ones where preserving it is hardest. A temporary stoma is often made to protect a low join while it heals. Some patients notice changes in bowel habit after rectal surgery, such as urgency or frequent stools.

Read more about rectal cancer treatment.

Benign Anal Conditions

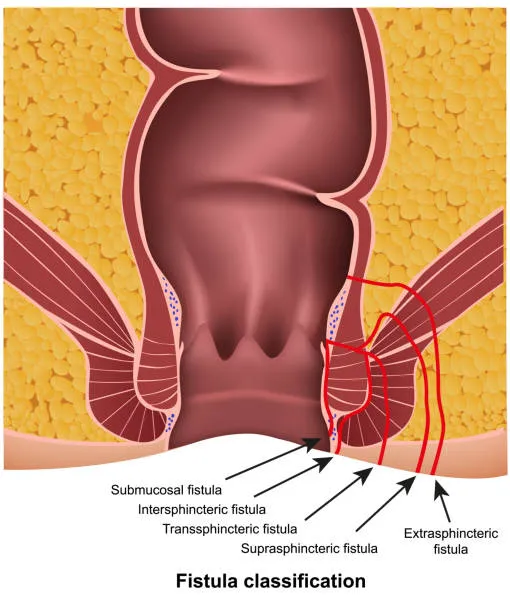
Cross‑section of the anal region showing fistula paths: submucosal, intersphincteric, transsphincteric, suprasphincteric, and extrasphincteric with surrounding muscles.

Anal Fistula

A fistula is a small abnormal channel connecting the inside of the anal canal to the skin nearby. It usually follows an infection or abscess. Fistulas are classified by how they pass through the sphincter muscles: intersphincteric, transsphincteric, suprasphincteric or extrasphincteric. The higher and more complex the tract, the greater the risk to continence if it is cut.

Read More..

Simple, low tracts can often be laid open. Complex or recurrent tracts need an MRI to find every branch and the internal opening, since a missed side tract is a common reason for recurrence. Options for complex fistula include a seton (a thread that drains the tract), sphincter-saving procedures such as LIFT or a flap, and other techniques, chosen for the individual tract. Fistulas linked to Crohn’s disease need a different approach, so the cause is checked first.
Read more about fistula treatment.

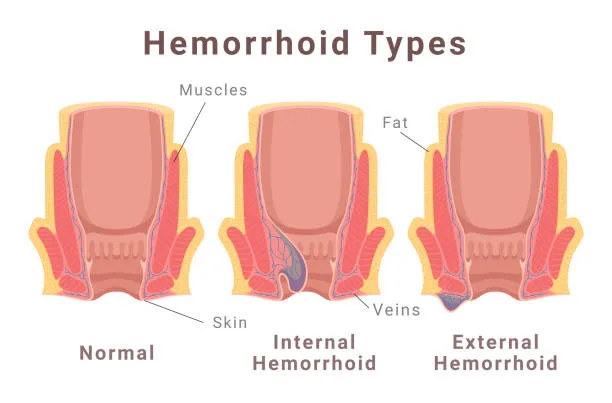
Diagram of hemorrhoid types: Normal, Internal hemorrhoid, and External hemorrhoid with labels for skin, fat, muscles, and veins.

Piles (Haemorrhoids)

Piles are swollen cushions of blood vessels in or around the anal canal. They are graded from I to IV, from piles that only bleed to those that stay outside and cannot be pushed back. Grade I and II usually respond to fibre, fluids, avoiding straining and medicines. Office procedures such as rubber band ligation or sclerotherapy suit some patients. Surgery, such as haemorrhoidectomy, is kept for larger piles or those that don’t respond. Bleeding should not be assumed to be piles, particularly after the age of 40 or with a change in bowel habit, since colorectal cancer can cause the same bleeding.
Read more about piles treatment.

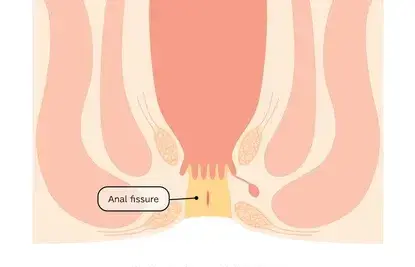
Illustration of the anal canal showing a small tear labeled 'Anal fissure' at the opening.

Anal Fissure

A fissure is a small tear in the lining of the anal canal, most often at the back midline. It hurts during and after a bowel movement, and there can be some bleeding. A fissure lasting more than about six to eight weeks is called chronic. First-line treatment is fibre, fluids and prescribed ointments that relax the sphincter. If these fail, options include botulinum toxin injection or a surgical procedure such as lateral internal sphincterotomy, which carries a small risk of affecting continence. A fissure in an unusual position should be examined for other causes. Read more about fissure treatment, or see anal fissure: when is surgery needed vs creams.

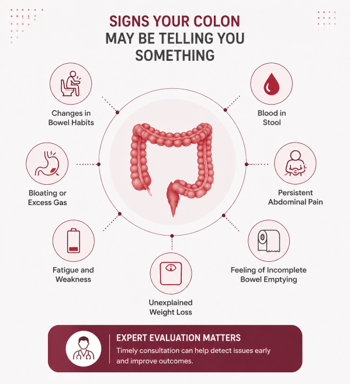
Symptoms That Need a Doctor’s Opinion

A change in bowel habits
Constipation or loose stools that don’t go away
Pain while passing stool
Pain in the abdomen or rectum
A lump or swelling near the anus
Weight loss with no clear reason, or anaemia

An abnormal colonoscopy report

Piles, fissure or fistula problems that keep coming back (see why anal fissures keep coming back after healing)

Plenty of these turn out to be harmless. A few don’t. You can’t tell which from the symptom alone, so if any of them last more than a couple of weeks, see a qualified doctor. People with a family history of colorectal cancer or polyps may need screening earlier than others, and the doctor can advise on timing.
Infographic: central colon illustration with six test panels around it (Colonoscopy, CT colonography, Stool tests, Blood tests, Endorectal ultrasound, Biopsy).

How Are Colorectal Conditions Diagnosed?

Infographic: central colon illustration with six test panels around it (Colonoscopy, CT colonography, Stool tests, Blood tests, Endorectal ultrasound, Biopsy).

Choosing the Operation: Open, Laparoscopic or Robotic

Treatment depends on the condition, the symptoms and the patient’s health. It can be as simple as a change in diet, or it can be an operation. Early or mild problems are often handled with fibre, better bowel habits and medicines, and a minimally invasive procedure may be considered for piles, fissures or fistulas if symptoms continue.
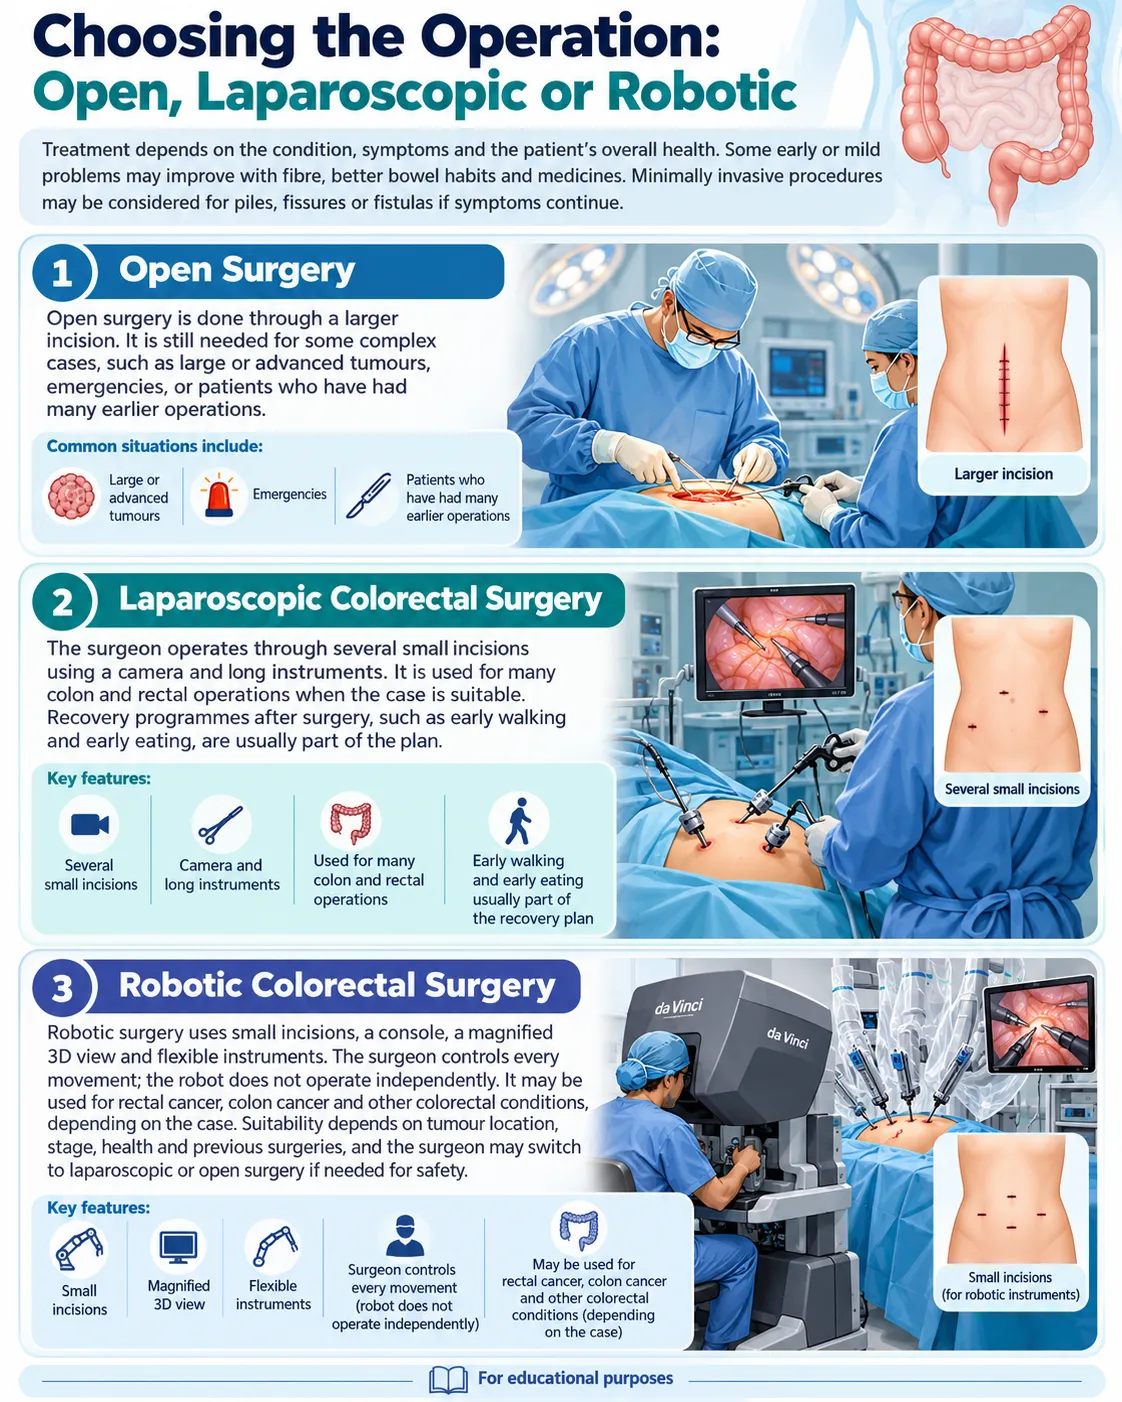
Infographic comparing Open, Laparoscopic, and Robotic colorectal surgery with surgeon teams and labeled incisions for each approach

When Is Colorectal Surgery Advised?

Medicines haven’t solved the problem
Cancer has to be removed
A growth or tumour has been found
Piles, fissures or fistulas keep returning
Symptoms are getting in the way of normal life

How Treatment Is Usually Planned

1. Examination

Symptoms and medical history are reviewed, and an examination is done.

2. Review of reports

Scans, colonoscopy results, biopsy reports and any earlier treatment are looked through.

3. Diagnosis and staging

For cancer, the stage is worked out. For benign conditions, the type and severity are confirmed.

4. Team discussion

Cancer cases are often discussed with the oncologist and radiologist.

5. Discussion of options

Each option is explained, including what it involves and its risks.

6. Surgery, if needed

The approach is chosen for the individual case, with safety and recovery in mind.

7. Follow-up

Check-ups continue after treatment. After cancer surgery, follow-up usually includes scans, blood tests and colonoscopy at set intervals.
Considering Colorectal Surgery costs? Speak with the clinic team to understand the likely treatment plan and associated expenses.

Dr. Shashank Agrawal: Treating Doctor

Qualifications

  • MBBS (2016)
  • MS, General Surgery (2019)
  • DrNB, GI Surgery (2022)

Registration

  • Delhi Medical Council: Reg. No. 9111
  • Uttar Pradesh Medical Council: Reg. No. 12711

Areas of practice

  • Colon and rectal cancer surgery (laparoscopic, robotic and open)
  • Complex and recurrent anal fistula
  • Piles and anal fissure
  • Other colorectal and gastrointestinal conditions

Plenty of these turn out to be harmless. A few don’t. You can’t tell which from the symptom alone, so if any of them last more than a couple of weeks, see a qualified doctor. People with a family history of colorectal cancer or polyps may need screening earlier than others, and the doctor can advise on timing.
Surgeon in blue scrubs and a hairnet uses an endoscope during a procedure, with an IV drip visible in the background.
Let’s hear it from our patients!

What Our Patients Say

Sabir Ahmad profile picture
Sabir Ahmad
1 year ago
I showed my son Mohammed Farhan to Dr. Shanshak Agarwal. Doctor sahib listened to our problem very well, saw the previous report and gave very good advice to our son which was better for us. The clinic staff is also very good. Our country needs such doctors a lot.
Kuber Singh profile picture
Kuber Singh
1 year ago
Experience doctor. Excellent knowledge. Polite behaviour.
Response from the owner
1 year ago
Thank you ! We are happy your kind words. We’re glad to hear that you had a positive experience
Amit chauhan profile picture
Amit chauhan
1 year ago
Good staff
Response from the owner
1 year ago
Thank you for your kind words ! We're glad to hear you had a positive experience with our staff.
Waseem Akram profile picture
Waseem Akram
1 year ago
Response from the owner
1 year ago
Thank you for five star rating.
Anuj Pandey profile picture
Anuj Pandey
1 year ago
Very polite and sincere behaviour towards the patient and visitors. Explain all details regarding your peoblem. One thing which makes him extraordinary is that he never in hurry mood. Listen all your problem with great patience. Very impressed with his attitude. I can not comment on his knowledge because i am not of that field but his confidence is sure enough to make him outstanding knowledge. I felt veruy much satisfy for my mother illness. A great thanks to him .
Response from the owner
1 year ago
Thank you for your kind words. We are truly glad you felt heard and supported during your visit and were satisfied with the treatment for your mother’s illness.
Ali Mehak profile picture
Ali Mehak
1 year ago
VERY good Doctor and excellent service good behaviour all unit indirapuram HEALIC HOSPITAL
Response from the owner
1 year ago
Thank you for visiting our gastroenterologist in Ghaziabad. We are glad to know that you are happy with the service.
Dr. Shashank is very cordial with patient. He observes very clearly. I am satisfied.
Response from the owner
1 year ago
Thank you for your kind words. We are glad to know that you are satisfied with the treatment.
Abhay Chaurasia profile picture
Abhay Chaurasia
1 year ago
Doctor treating patience very politely I'm glad to visit this Clinic.
Response from the owner
1 year ago
Thank you. We are happy to know you had a positive experience and felt comfortable during your visit.
Aman Singh profile picture
Aman Singh
2 years ago
I got my circumcision surgery done by Dr. Shashank agrawal This doctor is amazing doctor I prepared to consult the doctor Thank you for this doctor..
Response from the owner
2 years ago
Thank you for your kind words! We are happy to know that your circumcision surgery was successfully done by Dr. Shashank Agrawal.
Rajesh Kumar profile picture
Rajesh Kumar
2 years ago
I got my Koloid Surgery. Done by Dr. Shashank Agrawal This doctor is very good doctor Thank you Doctor...
Response from the owner
2 years ago
Thank you for your kind words! We are happy to know that you had a great experience and that your keloid surgery was successfully performed by Dr. Shashank Agrawal.

Frequently Asked Questions

What is colorectal surgery?

Surgery on the colon, rectum and anus to treat conditions such as colorectal cancer, anal fistula, piles and fissures. It may be open, laparoscopic or robotic, depending on the case.

Is rectal bleeding always piles?

No. Fissures, polyps and colorectal cancer can also cause it. That’s why it should be examined, not assumed.

Does every colorectal condition need surgery?

No. Many improve with medicines, lifestyle changes or minimally invasive procedures. Surgery is advised only when it’s needed.

Will I need a stoma after rectal cancer surgery?

Not always. Some patients need a temporary stoma to protect a low join while it heals, and a few need a permanent one. It depends on how close the tumour is to the sphincter and on the patient’s health.

Is robotic surgery better than laparoscopic surgery?

Not automatically. Both are minimally invasive, and the right choice depends on the condition, the patient and the case.

Can every colorectal operation be done laparoscopically or robotically?

No. Some cases still need open surgery, and sometimes the plan changes during the operation for safety.

How long is recovery?

It depends on the operation, the approach used and the patient’s general health.

How much does colorectal surgery cost?

It varies with the condition, the technique and the hospital.
Call Now Button" "